
Qelbree offers proven efficacy for children with ADHD1

Statistically significant reduction in ADHD symptom scores for children 6 to 11 years of age at EOS (6 weeks).1

Qelbree dosing: Straightforward titration in pediatric (ages 6-11 years) patients with ADHD1

Study P301: Titration through Week 1.1,3


Inclusion and study design

Study: P301
Age group: 6 to 11 years of age
mITT population: 460
Study medication: 100 mg capsule or matching placebo
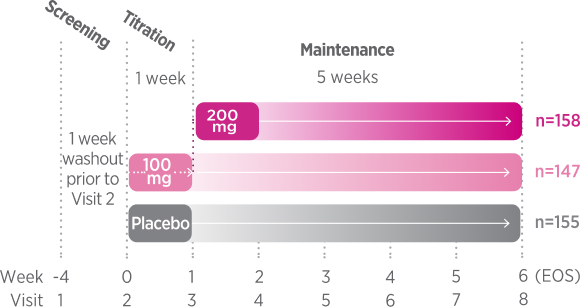
Phase III trial methodology: Randomized, DB, placebo-controlled, fixed-dose, parallel-group, multicenter study of children 6 to 11 years of age with ADHD (Study P301).1

Primary endpoint: CFB in ADHD-RS-5 Total Score at EOS (6 weeks).2

Proven efficacy in treating ADHD at EOS (n=460)1


Primary endpoint met: Significant improvement from baseline of the ADHD-RS-5 Total Score to EOS1,2

Study P301
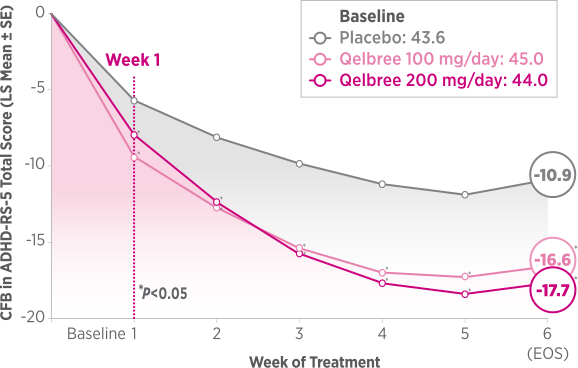
Study P301 results:

ADHD-RS-5 Total Score at EOS was significantly reduced with Qelbree vs placebo: The CFB in ADHD-RS-5 Total Score at EOS was -16.6 for Qelbree 100 mg/day, -17.7 for Qelbree 200 mg/day, and -10.9 for placebo.1

Symptom score reductions observed as early as week 1
 

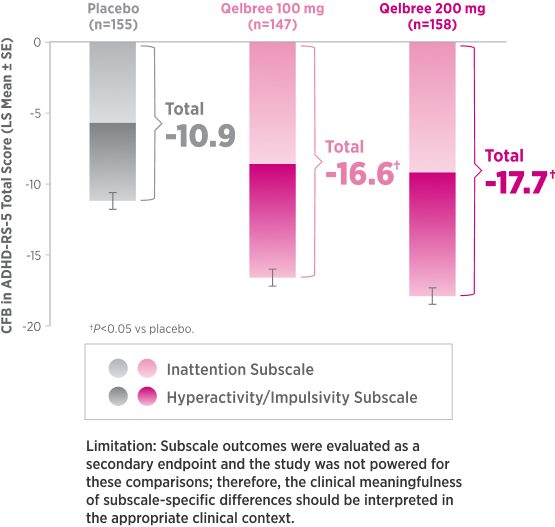
Secondary endpoint: Symptom score breakout for inattention and hyperactivity/impulsivity subscales at EOS (6 weeks)


Mean baseline ADHD-RS-5 Total Score was 45.0 for Qelbree 100 mg/day, 44.0 for Qelbree 200 mg/day, and 43.6 for placebo.2

CFB of ADHD-RS-5 inattention and hyperactivity/impulsivity subscales at EOS (6 weeks).
Study P303: Titration through 3 weeks

Inclusion and study design1,3

Study: P303
Age group: 6 to 11 years of age
mITT population: 301
Study medication: 100 mg capsule or matching placebo
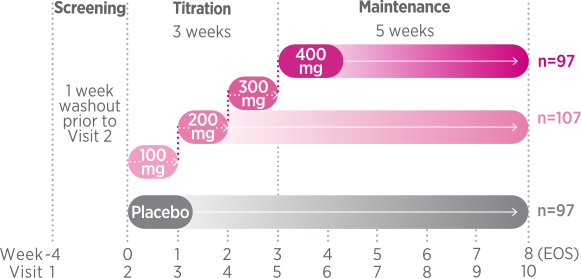
Phase III trial methodology: Randomized, DB, placebo-controlled, fixed-dose, parallel-group, multicenter study of children 6 to 11 years of age with ADHD (Study P303).1

Primary endpoint: CFB in ADHD‑RS‑5 Total Score at EOS (8 weeks).2

Proven efficacy in treating ADHD

Study P303 results: ADHD‑RS‑5 Total Scores were significantly reduced in pediatric patients treated with Qelbree vs placebo. The CFB in ADHD‑RS‑5 Total Score (LS mean ± SE) was -17.6 ± 1.43 for Qelbree 200 mg/day, -17.5 ± 1.52 for Qelbree 400 mg/day, and -11.7 ± 1.48 for placebo.1

Study P310: Qelbree OLE trial for children and teens with ADHD (ages 6-17 years)3


Long-term safety and efficacy data in pediatric populations

OLE study (P310): Subpopulation analysis, Qelbree 100 mg/day to 400 mg/day3

Methodology: Open-label, long-term, multicenter, flexible-dose study of Qelbree in children with ADHD who completed a Phase II/III trial of Qelbree 100 mg/day to 400 mg/day. Patients aged 6 to 11 years began with Qelbree 100 mg/day, adjusted weekly by 100 mg increments based on clinical response (100 mg/day to 400 mg/day). Patients aged 12 to 17 years began with Qelbree 200 mg/day, adjusted weekly by 200 mg increments based on clinical response (200 mg/day to 400 mg/day). The number of patients at each time point was as follows: entering OLE (n=749), completing optimization period (n=672), Month 3 (n=594), Month 6 (n=492), Month 9 (n=397), Month 12 (n=337), and Month 24 (n=200). The data presented here include patients who completed visits up to 24 months.3

Primary objective: Long-term safety data3

Secondary objective: Efficacy data during open-label use3

Qelbree daily dosage for children after 24 months in study3

A pie chart displays the percentage distribution of child ADHD patients across four daily dosage strengths: 43% for 400 mg/day, 26% for 300 mg/day, 25% for 200 mg/day, and 5% for 100 mg/day.

Children (n=148): Numbers may not total 100% due to rounding.

Pediatric OLE (ages 6-17 years), 100 to 400 mg subpopulation analysis3

Key outcomes from a 24-month pediatric open-label extension (OLE) study of Qelbree: mean dose was 311 mg/day at Month 24, with 70% of children and 65% of teens optimized at 300 mg/day or higher. No new safety signals were identified, and 8.2% discontinued due to adverse events.

OLE Study P310: Mean change from baseline in ADHD-RS-5 Total Score (overall mean baseline was 42.9)3‡
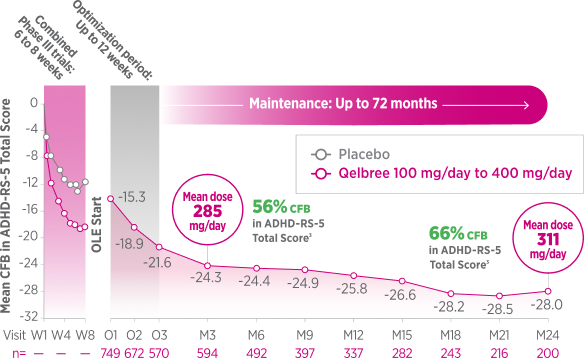
  • Data and calculations from patients in the OLE are descriptive only; there is no placebo group from which to draw a comparison of changes from baseline in ADHD-RS-5 Total Score or make any other long-term safety or efficacy conclusions3
  • OLE start: Patients 6 to 11 years of age started on Qelbree 100 mg/day; patients 12 to 17 years of age started on Qelbree 200 mg/day3

Based on 3 randomized, double-blind, placebo-controlled, parallel-group clinical trials that met the primary endpoint of data in ADHD-RS-5 total symptom score.

Abbreviations: ADHD, attention-deficit/hyperactivity disorder; ADHD-RS-5, Attention-Deficit/Hyperactivity Disorder Rating Scale, 5th Edition; AE, adverse event; CFB, change from baseline; DB, double blind; EOS, end of study; LS mean, least-squares mean; mITT, modified intent to treat; OLE, open-label extension; SE, standard error.

Discover more:

Stay informed

Get Qelbree email updates, savings information, and links to helpful resources for you and your patients.

Sign up 

IMPORTANT SAFETY INFORMATION

INDICATION

Qelbree (viloxazine extended-release capsules) is indicated for the treatment of Attention-Deficit/Hyperactivity Disorder (ADHD) in adults and pediatric patients 6 years and older.

IMPORTANT SAFETY INFORMATION

WARNING: SUICIDAL THOUGHTS AND BEHAVIORS

In clinical studies, higher rates of suicidal thoughts and behaviors were reported in [read more] patients with ADHD treated with Qelbree than in patients treated with placebo. Closely monitor all Qelbree-treated patients for clinical worsening and for emergence of suicidal thoughts and behaviors.

In clinical studies, higher rates of suicidal thoughts and behaviors were reported in patients with ADHD treated with Qelbree than in patients treated with placebo. Closely monitor all [read more] Qelbree-treated patients for clinical worsening and for emergence of suicidal thoughts and behaviors.

CONTRAINDICATIONS

  • Concomitant administration of a monoamine oxidase inhibitor (MAOI), or dosing within 14 days after discontinuing an MAOI, because of an increased risk of hypertensive crisis
  • Concomitant administration of sensitive CYP1A2 substrates or CYP1A2 substrates with a narrow therapeutic range

WARNINGS & PRECAUTIONS

  • Suicidal thoughts and behaviors: Closely monitor all Qelbree-treated patients for clinical worsening and emergence of suicidal thoughts and behaviors, especially during the initial few months of drug therapy, and at times of dosage changes
  • Heart rate, blood pressure increases: Qelbree can cause an increase in diastolic blood pressure and heart rate. Assess these measures prior to starting therapy, following increases in dosage, and periodically during therapy
  • Activation of mania or hypomania: Noradrenergic drugs may induce a manic or mixed episode in patients with bipolar disorder. Prior to initiating treatment with Qelbree, screen patients to determine if they are at risk for bipolar disorder. Screening should include a detailed psychiatric history, including a personal or family history of suicide, bipolar disorder, and depression 
  • Somnolence and fatigue: Patients should not perform activities requiring mental alertness, such as operating a motor vehicle or hazardous machinery, due to potential somnolence (including sedation or lethargy) and fatigue, until they know how they will be affected by Qelbree 

ADVERSE REACTIONS

The most common adverse reactions (≥ 5% and at least twice the rate of placebo for any dose) in patients 6 to 17 years were somnolence, decreased appetite, fatigue, nausea, vomiting, insomnia, and irritability, and in adults, insomnia, headache, somnolence, fatigue, nausea, decreased appetite, dry mouth, and constipation. 

PREGNANCY

There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to Qelbree during pregnancy. Healthcare providers are encouraged to register patients by calling the National Pregnancy Registry for Psychiatric Medications at 1-866-961-2388 or by visiting www.womensmentalhealth.org/preg. 

Please see full Prescribing Information, including Boxed Warning.

References:

1. Qelbree [package insert]. Rockville, MD: Supernus Pharmaceuticals, Inc. 2. Nasser A, Liranso T, Adewole T, et al. A phase III, randomized, placebo-controlled trial to assess the efficacy and safety of once-daily SPN-812 (viloxazine extended-release) in the treatment of attention-deficit/hyperactivity disorder in school-age children. Clin Ther. 2020;42(8):1452-1466. doi:10.1016/j.clinthera.2020.05.021 3. Data on file, Supernus Pharmaceuticals, Inc.

IMPORTANT SAFETY INFORMATION

INDICATION

Qelbree (viloxazine extended-release capsules) is indicated for the treatment of Attention-Deficit/Hyperactivity Disorder (ADHD) in adults and pediatric patients 6 years and older.

IMPORTANT SAFETY INFORMATION

WARNING: SUICIDAL THOUGHTS AND BEHAVIORS

In clinical studies, higher rates of suicidal thoughts and behaviors were reported in [read more] patients with ADHD treated with Qelbree than in patients treated with placebo. Closely monitor all Qelbree-treated patients for clinical worsening and for emergence of suicidal thoughts and behaviors.

In clinical studies, higher rates of suicidal thoughts and behaviors were reported in patients with ADHD treated with Qelbree than in patients treated with placebo. Closely monitor all [read more] Qelbree-treated patients for clinical worsening and for emergence of suicidal thoughts and behaviors.

CONTRAINDICATIONS

  • Concomitant administration of a monoamine oxidase inhibitor (MAOI), or dosing within 14 days after discontinuing an MAOI, because of an increased risk of hypertensive crisis
  • Concomitant administration of sensitive CYP1A2 substrates or CYP1A2 substrates with a narrow therapeutic range

WARNINGS & PRECAUTIONS

  • Suicidal thoughts and behaviors: Closely monitor all Qelbree-treated patients for clinical worsening and emergence of suicidal thoughts and behaviors, especially during the initial few months of drug therapy, and at times of dosage changes
  • Heart rate, blood pressure increases: Qelbree can cause an increase in diastolic blood pressure and heart rate. Assess these measures prior to starting therapy, following increases in dosage, and periodically during therapy
  • Activation of mania or hypomania: Noradrenergic drugs may induce a manic or mixed episode in patients with bipolar disorder. Prior to initiating treatment with Qelbree, screen patients to determine if they are at risk for bipolar disorder. Screening should include a detailed psychiatric history, including a personal or family history of suicide, bipolar disorder, and depression 
  • Somnolence and fatigue: Patients should not perform activities requiring mental alertness, such as operating a motor vehicle or hazardous machinery, due to potential somnolence (including sedation or lethargy) and fatigue, until they know how they will be affected by Qelbree 

ADVERSE REACTIONS

The most common adverse reactions (≥ 5% and at least twice the rate of placebo for any dose) in patients 6 to 17 years were somnolence, decreased appetite, fatigue, nausea, vomiting, insomnia, and irritability, and in adults, insomnia, headache, somnolence, fatigue, nausea, decreased appetite, dry mouth, and constipation. 

PREGNANCY

There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to Qelbree during pregnancy. Healthcare providers are encouraged to register patients by calling the National Pregnancy Registry for Psychiatric Medications at 1-866-961-2388 or by visiting www.womensmentalhealth.org/preg. 

Please see full Prescribing Information, including Boxed Warning.